Mental Health Screening
A brief screening to help identify areas of concern and connect patients with support
6 fieldsconversationalHealthcare
Fields included
Full name*
Short textEmail address*
EmailHow would you rate your current stress level? (1 = very low, 10 = very high)*
ScaleHow would you rate your sleep quality? (1 = very poor, 10 = excellent)*
ScaleWhat is your primary area of concern?*
Multiple choiceIs there anything else you'd like us to know before your consultation?
Long textLive Preview
Mental Health Screening
A brief screening to help identify areas of concern and connect patients with support
press Enter ↵

More Healthcare templates
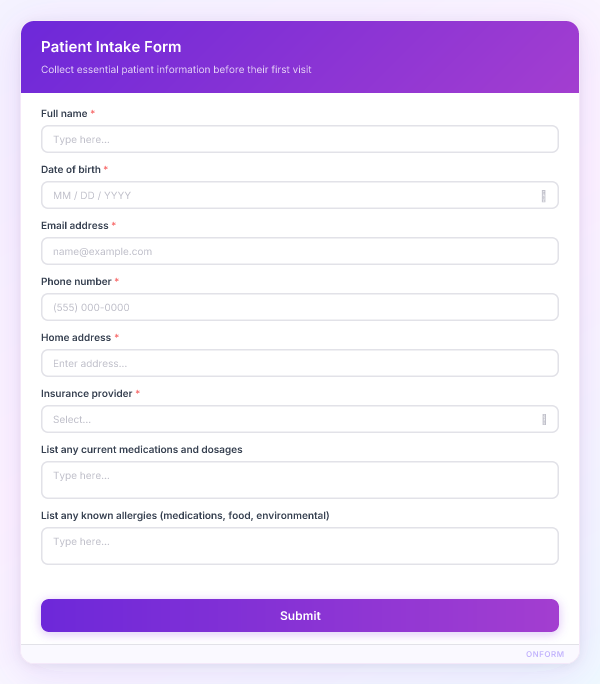
Patient Intake Form
Collect essential patient information before their first visit
8 fieldsHealthcare
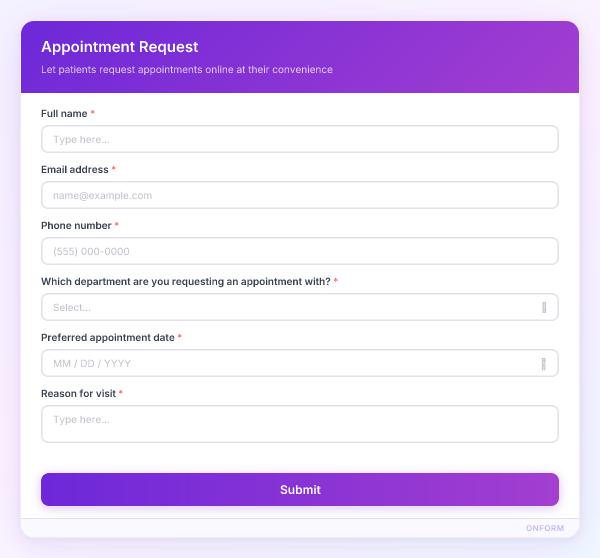
Appointment Request
Let patients request appointments online at their convenience
6 fieldsHealthcare
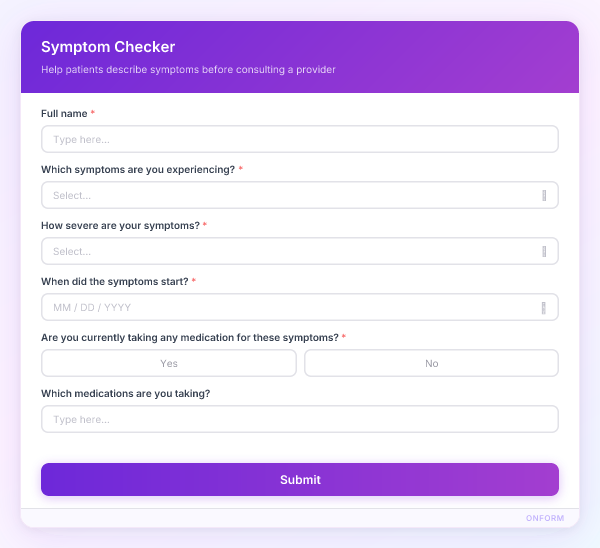
Symptom Checker
Help patients describe symptoms before consulting a provider
6 fieldsconversationalHealthcare